Radiology compliance reporting for compliance officers
Checklist for compliance officers to make radiology reports audit ready: required fields, PACS risk analysis, ACR RADS, MIPS dose capture, audit cadence

Radiology compliance reporting means producing auditable, structured final reports alongside documented system controls that regulators and payers can verify on demand. The immediate priority for any compliance officer is threefold: adopt structured templates that enforce required fields, run a PACS-specific risk analysis under HIPAA, and build an audit trail that can be exported without scrambling. Frameworks like ACR RADS give that structure a proven shape, and outsourcing partners such as AstraRad can supply signed, compliant reports when internal capacity falls short.
TL;DR:
- All required fields such as patient identifiers, clinical history, technique, findings, and impression must be systematically enforced in templates to ensure compliance.
- PACS security measures, including risk analysis, encryption, and detailed access logs, are crucial to protect imaging data from breach and comply with HIPAA standards.
- Breach reporting obligations depend on the affected individual count, with breaches of 500 or more needing immediate reporting within 60 days, while smaller breaches are reported annually.
- Regular, risk-based audits should be performed, with evidence including signed reports, access logs, and dose reports, to prevent common compliance failures like incomplete risk analysis or template drift.
- Outsourcing final report signing to specialized partners like AstraRad can help departments maintain compliance when internal capacity is limited or in-house controls are insufficient.
Table of Contents
- What every compliant radiology report must capture
- How do structured templates and RADS improve compliance?
- Does PACS security matter as much as report content?
- When does a breach trigger mandatory reporting, and what do quality measures require?
- How often should you audit, and what counts as evidence?
- How do you roll out a compliant reporting program?
- AstraRad's role in compliant final reporting
- What should you know about imaging data privacy day to day?
- What reporting standards apply to radiation dose tracking?
- How does compliance reporting connect to quality improvement?
- What compliance mistakes come up most often in radiology?
- A compliance officer's perspective
- A compliant reporting partner when capacity runs short
- FAQ
- Sources
What every compliant radiology report must capture
A compliant final report is not just a clinical document. It is a record that has to survive a payer audit, a HIPAA investigation, or a malpractice review years after the study was read. That means certain fields are not optional, no matter how busy the reading room gets.
- Patient and exam identifiers: full name, date of birth, medical record number, accession number, and exam date and time.
- Clinical history and indication: the reason for the study, pulled from the order, not inferred by the radiologist.
- Technique: modality, contrast use, protocol, and any deviations from standard technique.
- Findings: a systematic, organ-by-organ or region-by-region description, not a narrative summary alone.
- Impression: a clear, prioritized conclusion that a referring clinician can act on without rereading the findings.
- Radiologist identity and credentials: name, signature (electronic or wet), and license or board certification reference.
- Date and time of final sign-off, distinct from the date of preliminary interpretation if one existed.
Retention policies should follow the strictest applicable rule among state medical record laws, payer contract terms, and your own malpractice carrier's recommendations, since these frequently diverge and the longest requirement governs in practice. Many imaging centers default to seven years for adults and longer for pediatric studies, but you should confirm the figure against your state's specific statute rather than assume a national standard, since none exists.
Documentation quality also determines whether a claim survives a payer audit. Medical necessity reviewers look for a tight match between the ordering indication, the technique performed, and the impression rendered. A mismatch, such as a CT ordered for "abdominal pain" but reported with findings unrelated to that complaint and no explanation, is one of the more common triggers for claim denial or recoupment. The same fields that satisfy a Miller also feed quality measure submissions, which is why report structure and billing integrity are really the same project viewed from two angles.
How do structured templates and RADS improve compliance?
Structured reporting turns a list of required elements into something radiologists actually use consistently, rather than a policy that lives in a binder nobody reads during a busy shift. The American College of Radiology's Reporting and Data Systems standardize terminology and assessment categories across modalities like mammography, lung screening, and liver imaging, which reduces the variability that makes reports hard to audit or compare across radiologists.
When you design or revise a reporting template, three practices matter most:
- Build required fields into the template structure itself, so a radiologist cannot sign a report without completing them, rather than relying on memory or habit.
- Separate structured data from the free-text impression, giving radiologists room for clinical judgment while keeping the compliance-relevant fields machine-readable.
- Embed audit metadata automatically, including who created the template version, when it was last modified, and which fields are mandatory versus optional.
Template governance should not sit solely with IT or compliance. Radiologists who read the relevant modality need a voice in layout and wording, because templates imposed without clinical input tend to get bypassed through free-text workarounds that defeat the purpose. Version control matters here too: every template change should carry a date, an approver, and a brief rationale, so you can show an auditor exactly when a field was added and why.
Pro Tip: Keep a one-page change log per template family rather than burying revisions inside a shared document everyone edits differently.
Does PACS security matter as much as report content?
Yes, and regulators treat it that way. ACR, SIR, and SPR practice standards for interventional procedures specify that reports must be retrievable with the same timeliness and security as the images themselves, which means your PACS cannot be an afterthought in a compliance program built around report content alone.
PACS servers are a frequent point of failure because they are often internet-accessible for remote reading, and that exposure is exactly what OCR's settlement with Northeast Radiology centered on. The enforcement action cited an inaccurate and incomplete risk analysis of a PACS server holding protected health information as a core failure, not a one-off mistake.
A dedicated PACS risk analysis should inventory:
- Every modality and console that writes to the archive, including mobile and portable units.
- RDSR (radiation dose structured report) outputs and where they are stored.
- Archive replication paths, including any off-site or cloud backup destinations.
- Internet-facing endpoints used for remote radiologist access.
OCR enforcement actions repeatedly cite the failure to conduct an accurate, PACS-specific risk analysis as a root cause of HIPAA Security Rule violations, which makes this one analysis worth more compliance credit than almost any other single document in your file. Pair the risk analysis with regular vulnerability scans and penetration tests, documented access reviews, encryption at rest and in transit, and signed business associate agreements with every vendor that touches imaging data. For a structured approach to running that analysis, a practical HIPAA security risk analysis framework walks through the steps in a sequence auditors recognize.
When does a breach trigger mandatory reporting, and what do quality measures require?
Under the HIPAA Breach Notification Rule (45 CFR §§ 164.400-414), a breach of unsecured protected health information affecting 500 or more individuals must be reported to HHS without unreasonable delay and no later than 60 days after discovery. Breaches affecting fewer than 500 individuals are reported annually, typically within 60 days of the close of the calendar year. In either case, you need documented risk assessments showing how you determined whether an incident counted as a reportable breach, since the assessment itself becomes evidence during any follow-up review.
If you outsource reads to a teleradiology vendor, the covered entity remains on the hook for ensuring that vendor meets security and retention requirements, which is exactly why a signed business associate agreement with documented audit rights and acceptance testing belongs in every vendor contract.
Quality measures add a second layer of reporting obligation that often gets missed because it looks clinical rather than regulatory:
- CMS MIPS Measure 145 requires final fluoroscopy reports to document a radiation exposure index such as Ka,r, PKA/DAP, or peak skin dose.
- CMS MIPS Measure 360 and related measures require documentation of prior CT and cardiac nuclear study counts, along with follow-up recommendations for incidental findings like pulmonary nodules.
Templates that autopopulate dose indices directly from modality DICOM fields, rather than requiring a radiologist to transcribe them manually, cut errors and make quality measure capture far more reliable.
How often should you audit, and what counts as evidence?
Audit cadence should scale with volume and risk, not run on a fixed calendar that ignores both. High-volume modalities like chest X-ray and routine CT can usually tolerate quarterly random sampling, while interventional procedures, pediatric imaging, and anything tied to a prior compliance finding warrant monthly or even continuous review. Trigger-based audits, such as a sudden spike in amended reports or a payer denial pattern, should supplement the routine schedule rather than wait for the next cycle.
- Pull a representative sample combining random cases with targeted ones flagged by denials, complaints, or prior findings.
- Assemble the full evidence packet for each sampled case: the final signed report, PACS access logs, the radiation dose report where applicable, and the sign-off record with timestamp.
- Score each case against a simple rubric, checking for completeness of required fields, timeliness of sign-off, and consistency between indication and impression.
- Document findings in writing, even when the result is clean, since an audit with no paper trail is indistinguishable from an audit that never happened.
- Route deficiencies into a corrective action plan with a named owner, a remediation deadline, and a follow-up check to confirm the fix held.
How do you roll out a compliant reporting program?
Implementation works best as a phased rollout with clear ownership at each step, rather than a single policy memo distributed and forgotten.
- Assign a template owner, typically a lead radiologist who approves content changes before they go live.
- Give IT clear responsibility for PACS and EHR integration, including access controls and interface testing.
- Have your privacy officer sign off on any field that touches protected health information before deployment.
- Build a training cadence, ideally quarterly, so staff see template updates before they hit the live system, not after.
A reasonable rollout for a mid-size department runs 90 to 180 days: the first 30 for template design and clinician review, the next 60 for staged deployment and staff training, and the final 30 to 90 for the first formal audit cycle that validates the new structure actually works under real volume.
Pro Tip: Run your first audit cycle before the training rollout is fully complete, so you catch gaps while they are still cheap to fix.
AstraRad's role in compliant final reporting
Some departments running lean compliance teams find it simpler to route certain studies to a teleradiology partner for final signed reads rather than building every control in-house. We have subspecialists interpret and sign each report, matched to modality and body part, with peer review built into the workflow. Reports integrate directly with existing PACS systems, and deliverables include documentation such as dose indices where applicable, supporting the audit trail compliance teams need to assemble.
Rafael Vieira covers radiology compliance and reporting operations for this publication.
What should you know about imaging data privacy day to day?
Radiology data carries higher stakes than most protected health information because a single study, a chest CT or a mammogram, can contain more identifiable detail than a typical medical record entry, and it travels across more systems: the modality, the PACS, the reporting workstation, and often a cloud archive. Every one of those hops is a place encryption and access control can fail if nobody owns the full chain.
Minimum viable practice includes encrypting imaging data both at rest and in transit, restricting PACS access by role so a front-desk scheduler cannot open a diagnostic study, and logging every access event with enough detail to reconstruct who viewed what and when. Remote radiologist access, increasingly common with distributed reading groups, should run through a secure, audited connection rather than a shared login that defeats the purpose of access logging entirely.
Business associate agreements deserve the same scrutiny as the technical controls. A BAA that simply restates HIPAA language without specifying audit rights, breach notification timelines, and data return or destruction terms at contract end leaves gaps that surface only when something goes wrong. Review these agreements on the same cadence as your PACS risk analysis, since a vendor's security posture can change between contract renewals without anyone noticing.
What reporting standards apply to radiation dose tracking?
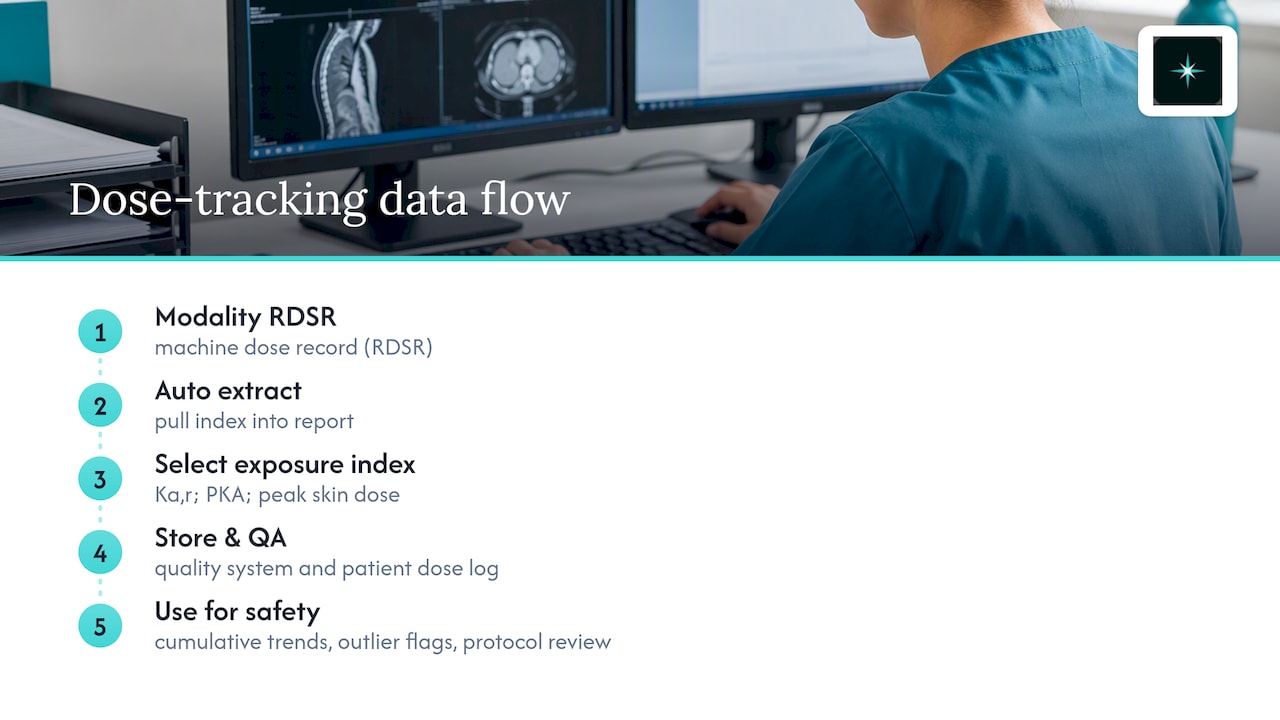
Dose monitoring has shifted from a quality nicety to a documented compliance requirement, driven largely by CMS MIPS Measure 145, which requires fluoroscopy reports to capture a named exposure index. The measure specification accepts several acceptable indices, including Ka,r, PKA (dose area product), or peak skin dose, so your template needs to document which one your department standardizes on and why.
The most reliable way to meet this requirement is pulling dose data directly from the modality's RDSR output rather than asking a technologist or radiologist to transcribe a number from a console screen. Manual transcription is where most dose-reporting errors originate, and it is also the easiest gap for an auditor to find, since the console log and the report rarely match exactly when a human copies the figure by hand.
Beyond the MIPS measure itself, dose tracking supports a broader radiation safety program: trending cumulative dose by patient over time, flagging outlier studies that exceed your department's established diagnostic reference levels, and feeding that data back to protocol review committees. None of that works if the dose index lives only in a console log that nobody exports into the reporting or quality system.
How does compliance reporting connect to quality improvement?
Compliance and quality improvement are often run as separate programs with separate meetings, which wastes the overlap between them. The same audit that checks whether a report includes a required field also tells you something about report quality, turnaround consistency, and whether templates are actually being used as designed.
Feed audit findings directly into your quality improvement committee's agenda rather than filing them separately. A pattern of missing dose indices, for example, is both a MIPS compliance gap and a radiation safety quality issue, and treating it as one problem instead of two saves meeting time and produces a more coherent corrective action plan. The same logic applies to turnaround time data: a STAT report that consistently misses its target is a quality concern for referring clinicians and, depending on payer contract terms, potentially a compliance issue too.
Practices that route compliance audit data into existing peer review and quality committees tend to catch systemic issues faster than those running the two functions on parallel, disconnected tracks. The structural fix is simple: put compliance metrics on the same dashboard as clinical quality metrics, reviewed by the same group, on the same cadence.
What compliance mistakes come up most often in radiology?
A few patterns show up repeatedly across departments, and most are preventable with the structural fixes already covered here rather than requiring new policy.
The most common gap is a PACS risk analysis that exists on paper but was never actually completed for the specific servers and remote access points in use, which is precisely the failure cited in OCR's enforcement action against Northeast Radiology. A second frequent issue is template drift, where radiologists quietly bypass structured fields through free-text workarounds because the template felt cumbersome and nobody enforced its use. A third is incomplete business associate agreements with imaging vendors, often missing specific audit rights or breach notification timelines rather than lacking a BAA altogether.
Electronic signature practices also trip up departments that assume any digital sign-off counts as compliant. A clear framework for US electronic signature requirements helps clarify what makes a signed report legally defensible versus merely convenient. Finally, audit trails that exist in theory but cannot actually be exported on demand, because nobody tested the export function until an auditor asked for it, undermine an otherwise solid program. A good audit trail does more than log access. For a clearer sense of what an audit trail should actually prove when a surveyor or regulator asks for it, treat the export test as part of your routine audit cycle, not a one-time setup task.
A compliance officer's perspective
The departments that stay out of trouble are not the ones with the thickest policy binder. They are the ones that treat the PACS risk analysis, the structured template, and the audit trail as one connected system, tested regularly, rather than three separate projects that only meet during an actual investigation.
Rafael Vieira
A compliant reporting partner when capacity runs short
When internal capacity cannot keep pace with compliant documentation, AstraRad's board-certified subspecialists deliver signed, audit-ready reports integrated directly with your PACS.
FAQ
What are the guidelines for radiology reporting?
Radiology reporting guidelines require a complete final report with patient identifiers, clinical indication, technique, findings, impression, and a credentialed sign-off, retrievable with the same security as the underlying images under ACR practice standards. Structured reporting systems like ACR RADS standardize terminology for specific modalities, reducing variability across radiologists.
What is an example of compliance reporting?
A fluoroscopy report documenting a radiation exposure index such as Ka,r or PKA, as required by CMS MIPS Measure 145, is a concrete example of compliance reporting in radiology. Another is a breach risk assessment documented and submitted to HHS within the timelines set by the HIPAA Breach Notification Rule.
What are the 7 elements of healthcare compliance?
Common healthcare compliance frameworks reference seven core elements: written policies and procedures, a designated compliance officer, effective training, open communication lines, internal monitoring and auditing, consistent enforcement of standards, and prompt corrective action. Definitions vary slightly by source, but these elements map directly onto a radiology department's risk analysis, template governance, and audit cycle.
What are the 5 key areas of compliance?
For radiology specifically, the key areas are patient privacy and data security, accurate and complete documentation, radiation safety and dose tracking, billing and medical necessity integrity, and ongoing audit and monitoring. Each area ties back to the structured reporting and PACS risk analysis practices described throughout this guide.
Sources
Recommended
Related on AstraRad
- Resources
Top teleradiology companies 2026: what each one states
Teleradiology companies buyers shortlist in 2026, listed alphabetically with what each states on its own site, linked and dated, and how to compare them.
- Resources
Radiology image sharing policy maps HIPAA to PACS
Vendor agnostic policy for hospital admins: map HIPAA and BAA to PACS/DICOM controls, verify DICOM TLS, and use 5 step onboarding checklist.
- Resources
Teleradiology companies in the USA: what US-based means
What US-based actually means when a teleradiology company claims it: onshore vs offshore reads, the Medicare payment rule, and state licensing checks.
Put a radiologist's name on your next read.
Tell us your modalities and monthly volume. A complete per-report rate card, with turnaround tiers and SLA terms in writing, lands in your inbox within one business day.