Radiology template governance: a buyer's guide
Radiology template governance explained for US buyers: who approves templates, how to version them, and what to require from a teleradiology contract.

Radiology template governance is the set of rules that decides who writes, approves, changes and retires the report templates your radiologists use. Good governance keeps reports consistent across readers and sites, and it keeps template changes traceable. For hospitals, imaging centers and radiology groups that outsource reads, it also defines what your teleradiology contract must say about report format.
- The Canadian Association of Radiologists' 2025 position statement says departments should maintain template libraries and coordinate changes to sanctioned templates.
- The RSNA library offers more than 200 free report templates built on RadLex and other standard terminologies.
- The IHE Radiology MRRT profile, introduced in 2013, gives templates a vendor-neutral exchange format.
- The ACR practice parameter on communication of diagnostic imaging findings (2025) lists the report elements a standardized report should include.
- AstraRad routes every study to a board-certified subspecialist, and 1 in 20 reports is independently double-read, blind, for peer review.
TL;DR
- Governance means named owners, a written approval path, version control and a periodic audit for every report template.
- Intended users, meaning the radiologists who read with the template, should approve it and be able to adapt it to the patient in front of them.
- Templates should live inside your existing PACS and reporting workflow, not in a side document.
- When you outsource reads, put template expectations, change requests and quality review into the contract and SLA.
Table of Contents
- What is radiology template governance?
- Why does radiology template governance matter for standardized reporting?
- What should a radiology reporting template include?
- Who should approve and maintain radiology templates?
- Where does AstraRad fit in template governance?
- How do you validate templates and manage version control?
- How do templates integrate into PACS and interoperable workflows?
- How do you audit template use and report quality?
- What should a teleradiology contract say about templates and reports?
- Ready to put your report standard under contract?
- FAQ
- Sources
What is radiology template governance?
Radiology template governance is a formal process for owning, approving, versioning and auditing the report templates a radiology practice uses. A report template is a pre-built structure of headings and prompts that a radiologist fills in while dictating or typing a report. Governance answers four questions: who may create a template, who signs off on it, how changes are released, and how you know the template is being used correctly.
Without those answers, templates drift. One site adds a field, another deletes a section, a third keeps a ten-year-old version of a chest CT template. The result is reports that look different depending on who read the study and where, which makes comparison and downstream use harder for referring clinicians.
Three terms come up repeatedly in this work:
- Structured reporting is a method of writing radiology reports with a consistent organization and, where possible, standard terminology, so the content is easier to read, compare and reuse.
- A template library is the managed collection of approved templates, organized by modality, body part and study type.
- MRRT is the IHE Radiology profile, Management of Radiology Report Templates, that defines a standard file format for creating and sharing structured reporting templates.
Why does radiology template governance matter for standardized reporting?
Template governance matters because standardized reports are only as consistent as the templates behind them. The Canadian Association of Radiologists' 2025 position statement on structured reporting says structured reporting improves consistency and reduces errors, and that departments should maintain template libraries and coordinate changes to sanctioned templates.
For a buyer, the practical effects show up in four places:
- Clinical clarity. Referring physicians learn where to find the impression and the comparison studies, so they read faster and miss less.
- Risk management. When a template is changed, you can show who approved the change and when. That matters if a report is ever questioned.
- Operational predictability. Consistent templates reduce the editing and addenda that slow down final signature.
- Vendor management. If you use an outside reading group, governance gives you a clear standard to hold that group to.
Governance is not a push for rigid, one-size-fits-all forms. The same guidance recognizes that templates should remain flexible. The point is a controlled starting structure, with room for the radiologist's judgment.
What should a radiology reporting template include?
A standardized radiology report should include patient demographics, relevant clinical information, the procedure and materials used, findings, potential limitations and clinical issues when appropriate, comparison studies, and an impression or conclusion. That list comes from the ACR practice parameter for communication of diagnostic imaging findings, updated in 2025.
Use it as the baseline for every template in your library. A practical way to apply it is a section checklist that every template must pass before approval:
| Report element | What the template should do |
|---|---|
| Demographics | Pull patient and exam identifiers from the order, not from free text |
| Clinical information | Prompt for the indication and relevant history |
| Procedure and materials | Record the technique, and contrast where used |
| Findings | Organize by anatomy or system, with prompts for pertinent negatives |
| Limitations | Provide a place to note motion, incomplete coverage or other constraints |
| Comparison | Name the prior studies used, or state that none were available |
| Impression | Give a concise conclusion and any follow-up recommendation |
Two cautions belong in your governance policy. First, the ACR states that its practice parameters are educational tools rather than inflexible rules, and that professional judgment must guide their application to specific patient circumstances, as noted in the ACR-SIR-SPR practice parameter. Second, over-built templates cause trouble. Users must be able to customize, remove or replace sections to fit the patient, a point stressed in RSNA guidance on implementing standardized structured reporting.
Who should approve and maintain radiology templates?
The people who will use a template should approve it, and a designated radiologist or small team should coordinate changes with leadership support. This is the approach in the CAR position statement, which also recommends involving radiologists, technologists and other key stakeholders in template design and implementation.
The RSNA's guidance on implementation adds that successful change management engages early adopters as champions, gathers broad input during design, and secures visible endorsement from departmental leadership. It also observes that organizational challenges, such as changing roles and values, often outweigh technical ones. Plan for the people side first.
A workable role structure looks like this:
| Role | Responsibility | Typical owner |
|---|---|---|
| Template owner | Coordinates requests, drafts changes, keeps the library current | Designated radiologist or small committee |
| Clinical reviewers | Approve content for their subspecialty | Radiologists who read that modality or body part |
| Referring clinician input | Confirms the report answers their questions | Representatives from high-volume referring services |
| Technical steward | Loads, tests and releases templates in the reporting system and PACS | PACS administrator or imaging informatics lead |
| Executive sponsor | Backs the standard and resolves disputes | Department chair or medical director |
| Compliance contact | Confirms records of changes meet policy | Compliance or quality officer |
Write the approval path into a short policy. One page is enough: who may request a change, who reviews it, how long review should take, and how the release is announced to readers.
Where does AstraRad fit in template governance?
AstraRad is a US teleradiology service that delivers final signed reports read by board-certified subspecialists. We publish this guide because template governance becomes a procurement question the moment you outsource reads, and we sell teleradiology services to hospitals, imaging centers and radiology groups. That is a commercial interest, and you should weigh the article with it in mind.
What we can say about our service is specific. Every study is routed to a subspecialist matched to the modality and body part, across ten subspecialties and twelve study types. Reads are performed inside the United States on scheduled shifts, 24/7/365. Reports go straight into your existing PACS with no extra portal, and the integration is DICOM conformant. You can see how a study moves from your PACS to a signed report on our How Teleradiology Works page, and the full list of modalities is on our teleradiology services page.
What we do not claim is that any outside reading group should replace your own governance. You still own your standards. The sections below show what to put in front of any teleradiology provider, including us, so those standards carry through to the final report.
How do you validate templates and manage version control?
Validate a template with two checks, clinical review and technical testing, then release it under a version number. Clinical review confirms the content is correct and complete for the study type. Technical testing confirms the template loads and populates correctly in your reporting system. Version control then records what changed, who approved it and when it went live.
Published work on template libraries shows what this looks like in practice. In a study converting RSNA templates to the MRRT format, each template underwent editorial review by two radiologists with more than 20 years of experience and technical validation for correct HTML5 and MRRT syntax. You do not need to match that exact process, but the two-track pattern is a sound model: a clinician checks meaning, a technician checks function.
A practical release checklist:
- Request. A reader or referring clinician submits the change with a reason.
- Draft. The template owner prepares the revision and marks what changed.
- Clinical review. Radiologists in that subspecialty approve or return it.
- Technical test. The PACS or reporting administrator tests it in a non-production environment.
- Release. The new version gets a number and date, and readers are notified.
- Retire. The old version is archived, not deleted, so past reports can be traced to the template in force at the time.
Keep a change log for each template. A simple table with version, date, approver and summary of change is enough, and it is the first thing an auditor or a quality committee will ask to see.
How do templates integrate into PACS and interoperable workflows?
Templates work best when they sit inside the reporting tools your radiologists already use. The CAR statement recommends integrating templates into existing reporting systems and workflows, including PACS, so a radiologist can select a template for a study and populate its sections without leaving the workflow.
For sharing across organizations, the standard to know is MRRT. The IHE Radiology MRRT profile, introduced in 2013, provides an industry-standard format for creating, transporting and using structured reporting templates, and it supports vendor-neutral exchange between radiology information systems, according to the MRRT conversion study. The same source notes that the RSNA developed more than 200 freely available templates, a useful starting library if you are building one.
When you evaluate any reading arrangement, ask these integration questions:
- Does the report return to your PACS as a final signed report, or to a separate portal your staff must check?
- Which interface standards are used for orders and results, such as DICOM and HL7?
- Can your approved templates, or their section structure, be used by the outside readers?
- Who is responsible for loading and testing a template change on each side?
Our own answer to the first question is that reports are delivered into your existing PACS with no extra portal. Our MRI teleradiology reporting page shows how that applies to one of the most template-dependent modalities.
How do you audit template use and report quality?
Audit template use by sampling signed reports against the approved template and scoring them on a short, fixed checklist. The goal is to learn whether readers use the current version, whether required sections are complete, and whether the impression is clear. Repeat the audit on a schedule so you can see trends rather than one-off findings.
The ACR points to the same logic in its work on breast imaging. Its coverage of BI-RADS v2025 says the auditing and outcomes monitoring sections let practices benchmark performance against national standards. The lesson carries over to template governance: measure against a defined standard, not against impressions.
A starting audit scorecard:
| Check | Question | Frequency |
|---|---|---|
| Version | Was the current approved template used? | Each audit cycle |
| Completeness | Are all required sections filled in? | Each audit cycle |
| Comparison | Are prior studies named, or their absence stated? | Each audit cycle |
| Impression | Is it concise and does it carry any follow-up recommendation? | Each audit cycle |
| Addenda | Did the report need correction after signature? | Reviewed with quality committee |
If you outsource reads, peer review is part of this picture. At AstraRad, 1 in 20 reports is independently double-read, blind, for peer review. Ask any provider how its peer review works and what it reports back to you. Our subspecialist radiologists page explains how readers are matched to studies.
What should a teleradiology contract say about templates and reports?
Your contract and SLA should state the report standard, the turnaround commitments, the change process and the review process in writing. Procurement teams often focus on price and turnaround and leave report format to chance. Governance closes that gap by turning your template standard into contract language.
| Contract topic | What to specify |
|---|---|
| Report deliverable | Final signed report at every tier, including overnight |
| Report structure | Required sections, based on your approved templates and the ACR elements |
| Turnaround | Committed times by tier, with the measurement start and end points defined |
| Credentialing | Board certification, subspecialty match and state licensure for each study |
| Change control | How you request a template change, who approves it, and the release timeline |
| Quality review | Peer review method, sampling rate and what is reported to you |
| Data protection | A signed BAA and the provider's HIPAA-aligned safeguards |
| Integration | Delivery into your PACS, DICOM conformance, no extra portal |
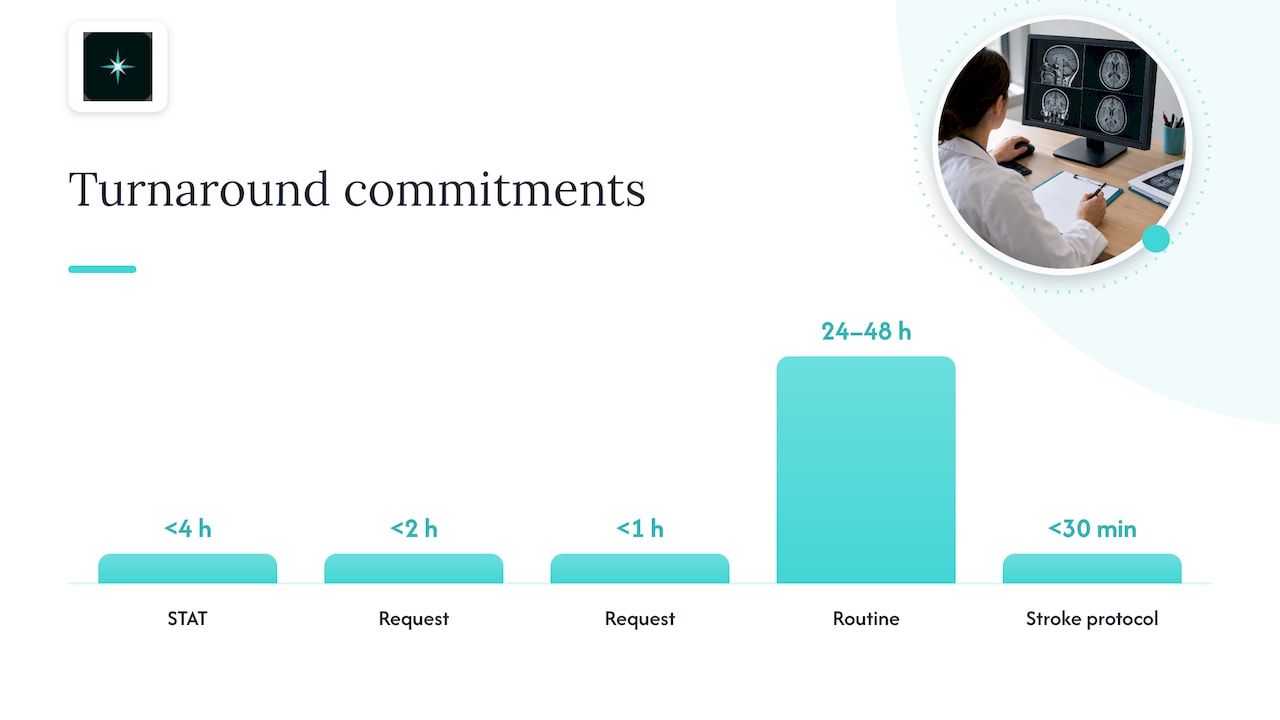
Our contract commitments follow this shape. Turnaround is committed by contract and measured from last-image arrival to radiologist signature. STAT is under 4 hours, with under 2 hours or under 1 hour on request. Routine is 24 to 48 hours, and the stroke protocol is under 30 minutes. Radiologists are licensed in all 50 states. We are HIPAA aligned and work as a business associate under a signed BAA.
A coverage plan with SLA terms in writing follows the discovery call, so you can review the language against your governance policy before you sign.
Ready to put your report standard under contract?
AstraRad is a US teleradiology service that delivers final signed reports read by board-certified subspecialists. Pricing is per report with no minimums, and the first signed report arrives within 10 business days of countersignature.
If you want to compare a provider against your own template and SLA requirements, request the per-report rate card, delivered within one business day, or book a discovery call to walk through your templates, modalities and PACS setup.
FAQ
What is the difference between a template and structured reporting?
A template is a pre-built form that guides how a report is written. Structured reporting is the broader method of organizing report content consistently, often with standard terminology. Templates are the main tool for achieving it, and governance keeps those templates controlled.
How often should radiology templates be reviewed?
Set a fixed review cycle, such as annually, and add reviews whenever a guideline or reporting system changes. Published guidance stresses coordinated change rather than a specific interval, so choose a cadence your template owner can sustain and record it in your policy.
Can an outside teleradiology provider use our templates?
It depends on the provider and your reporting setup, so raise it early. Ask how your required sections will be reflected in the final signed report, who loads changes, and how both sides test them. Put the agreed answer in the contract.
Where can we find free radiology report templates?
The RSNA offers a library of more than 200 report templates built on RadLex and other standard terminologies, and the library has been converted to the MRRT format. Treat them as a starting point and run them through your own approval process.
Does AstraRad require volume minimums?
No. AstraRad is a US teleradiology service that delivers final signed reports read by board-certified subspecialists, and pricing is per report with no minimums. You can request the full rate card at /pricing.
Sources
- Canadian Association of Radiologists, Position Statement on Structured Reporting (2025)
- ACR Practice Parameter for Communication of Diagnostic Imaging Findings (2025)
- ACR-SIR-SPR Practice Parameter for the Reporting and Archiving of Interventional Radiology Procedures (2024)
- RSNA, Strategies for Implementing a Standardized Structured Radiology Reporting Program (2018)
- Conversion of Radiology Reporting Templates to the MRRT Standard (PubMed Central)
- ACR Bulletin, BI-RADS v2025 Guide to Breast Imaging
Related on AstraRad
- Resources
DICOM TLS encryption: how to secure imaging traffic
DICOM TLS encryption secures imaging traffic in transit, covering profiles, TLS versions, certificates, and checks hospitals and imaging centers need.
- Resources
Teleradiology compliance checklist for US buyers
Use this teleradiology compliance checklist to vet licensure, credentialing, HIPAA safeguards, BAA terms and SLA language before you sign a contract.
- Resources
Turnaround variance root causes in radiology reporting
Turnaround variance root causes in radiology reporting include definitions, staffing, modality mix and handoffs, and here is how to find each one.
Put a radiologist's name on your next read.
Tell us your modalities and monthly volume. A complete per-report rate card, with turnaround tiers and SLA terms in writing, lands in your inbox within one business day.